Orthopedic injection types span a range of treatments used to manage joint, muscle, and bone pain — from short-acting anti-inflammatories to biologic solutions derived from a patient’s own blood or tissue. Clinicians can match the right option for each patient by comparing mechanism, administration, dosing, and side-effect profile across categories.
Medica Depot’s coverage of orthopedic injection types spans corticosteroid, hyaluronic acid, platelet-rich plasma, stem cell, and prolotherapy categories. Providers who buy orthopedic injections can review this article to learn how these treatments differ and where each tends to fit into a treatment plan.
Key Takeaways
- Orthopedic injection types differ substantially in mechanism, from anti-inflammatory corticosteroids to regenerative orthobiologics like PRP and stem cell products.
- Administration technique and dosing schedules vary by injection type, joint treatment area, and condition.
- Preparation, risk profile, and insurance coverage are inconsistent across types of joint injections, which should factor into patient counseling and product selection.
About: Medica Depot is your trusted all-in-one supplier, offering a range of high-quality medical injectables and supplies. We offer a worry-free experience in searching for the best and most popular products on the market, like hyaluronic acid gel injections. Whether for health professionals, plastic surgeons, dermatologists, licensed estheticians, or other specialists, we can offer genuine, brand-name products you may need. With Medica Depot, we prioritize serving you better to improve the patient’s quality of life.
What Are Orthopedic Injection Types? An Overview
Types of orthopedic injections are grouped by what they deliver into or around the joint. These include synthetic anti-inflammatory compounds, viscosupplements, blood-derived biologics, cell-based products, and irritant solutions intended to trigger a healing response.
The categories are not interchangeable, since they act through different biological pathways. A corticosteroid targets inflammation quickly, while a hyaluronan viscosupplement is thought to modify joint lubrication and cartilage biology over weeks.
Choosing among the types of joint injections means weighing onset of relief, duration of benefit, cost, and evidence strength for the specific condition. For medical professionals building a broader treatment protocol, injections are typically considered alongside physical therapy, activity modification, and bracing as part of orthopedic treatment, reserved for patients needing more targeted symptom control.
Corticosteroid Injections: Mechanism, Administration, and Tradeoffs
Corticosteroid injections suppress the local inflammatory cascade — reducing capillary permeability, limiting the accumulation of inflammatory cells, and decreasing swelling, heat, and tenderness in the affected joint [1].
Common injection preparations include methylprednisolone acetate, triamcinolone hexacetonide, and triamcinolone acetonide. Different formulations show broadly similar effectiveness, and there is insufficient evidence to strongly recommend one over another [1].
Corticosteroids offer a comparatively fast onset of anti-inflammatory relief. Duration is typically shorter than that of viscosupplements or PRP, though some patients experience benefit for a few months, with overlap possible against shorter HA data [1]. Practitioners administer intra-articular or peri-articular injections using either landmark technique or image guidance; ultrasound is more accurate than palpation, and image guidance may be preferred in higher-BMI patients or after a failed landmark attempt (Grade C recommendation) [1].
Because of concerns about cumulative joint effects, injections into a single joint are typically limited to a small number per year — a dosing ceiling worth weighing against longer-interval options like HA or PRP.
Hyaluronic Acid (HA) Gel Injections: How Do They Compare?
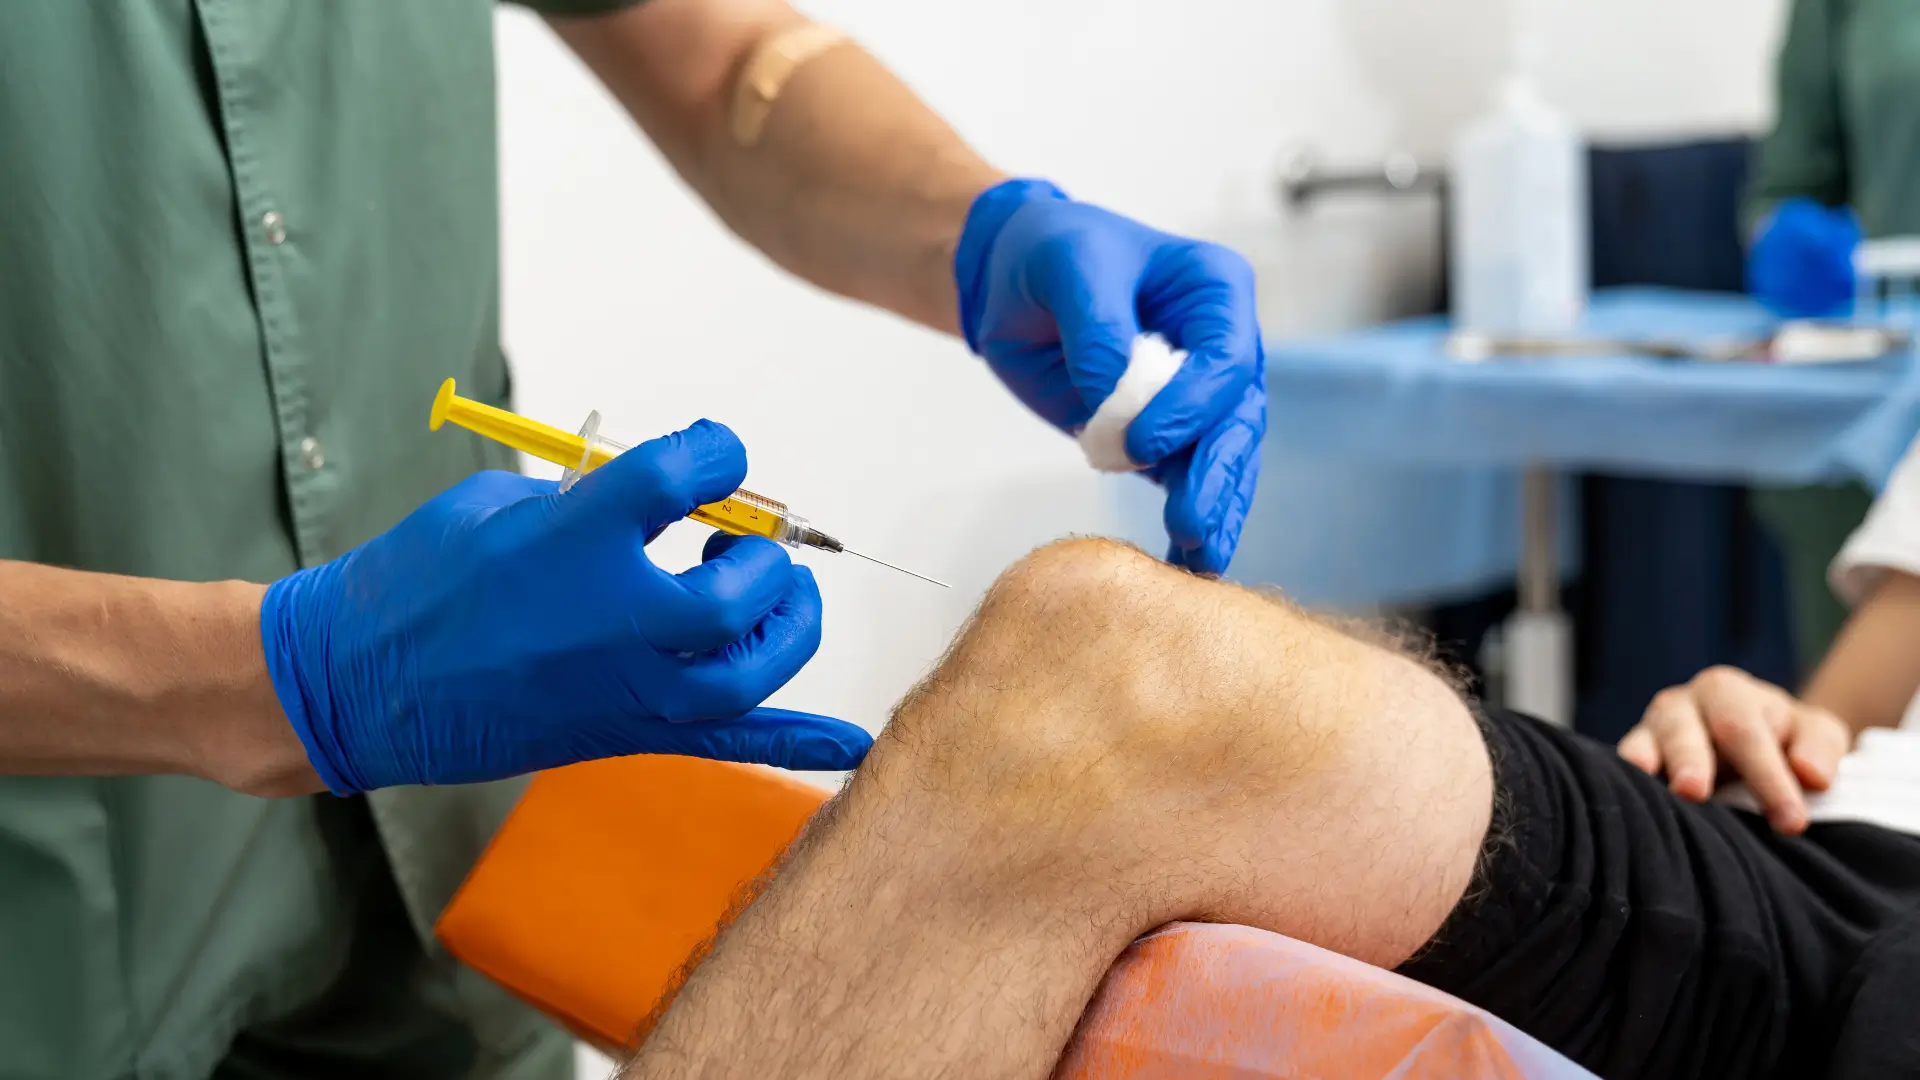
Hyaluronic acid gel injections, or viscosupplementation, involve delivering hyaluronan into the affected joint. Products in this category are viscosupplement (hyaluronan) preparations of varying molecular weight and cross-linking — some are single-shot cross-linked gels, others are intermediate-molecular-weight solutions delivered as a short weekly series.
HA is found naturally within the joint and gives synovial fluid its viscoelastic properties. Proposed benefits include chondroprotection, glycosaminoglycan synthesis, anti-inflammatory activity, and direct analgesic action [2].
In the US, HA products are FDA-approved for knee osteoarthritis pain in patients who have failed conservative non-pharmacologic therapy and simple analgesics [3]. Coverage rules can be stricter than the on-label indication: Palmetto GBA’s Medicare Local Coverage Determination L39260, for example, may also require documented failure of intra-articular corticosteroid before HA is covered [4]. That distinction matters — L39260 governs coverage, not FDA approval.
Compared with corticosteroids, HA gel injections tend to have a slower onset but longer-lasting relief, typically measured in months. Compared with orthobiologics like PRP, HA has a longer regulatory track record and more standardized dosing. Side effects are usually limited to mild, transient injection-site reactions.
Platelet-Rich Plasma (PRP) Injections: What Sets Them Apart?
Platelet-rich plasma injections take a different approach from other treatments. Rather than a synthetic or gel-based compound, PRP is prepared from the patient’s own blood, concentrated through centrifugation to isolate a higher density of platelets and their growth factors.
The concentrate is reintroduced into the target tissue to stimulate repair, with bioactive proteins such as platelet-derived growth factor, transforming growth factor-beta, and insulin-like growth factor thought to drive the response [5]. This autologous, growth-factor-driven mechanism sets orthopedic PRP injections apart from corticosteroids and HA, positioning PRP as a regenerative treatment option.
Typical preparation involves drawing and processing blood at the point of care. Dosing protocols vary widely, depending on centrifugation method, platelet concentration, and whether leukocytes are included. PRP also costs meaningfully more per injection than a corticosteroid injection.
The evidence base is mixed overall, with heterogeneous protocols across studies. In one narrative review of orthopedic PRP applications, signals were strongest in knee osteoarthritis and lateral epicondylitis, with inconsistent or minimal benefit reported in rotator cuff repair, patellar and Achilles tendinopathy, hamstring injury, ACL reconstruction, and medial epicondylitis [5].
Stem Cell and Other Orthobiologic Injections: Where Do They Fit?
Mesenchymal stem cell preparations, bone marrow aspirate concentrate, and amniotic or umbilical tissue products represent the newest, most regulatory-sensitive category of orthopedic injection types. This group is positioned as regenerative — intended to modulate inflammation and support tissue repair at a cellular level.
Regulatory status here is often misunderstood. FDA-approved hematopoietic progenitor cell products derived from cord blood are indicated for disorders affecting the blood-forming system, not orthopedic conditions. Ryoncil (remestemcel-L), the first FDA-approved mesenchymal stromal cell therapy, is indicated for pediatric steroid-refractory acute graft-versus-host disease — again, not orthopedic. No cell-based product currently carries FDA approval for osteoarthritis or musculoskeletal repair. Some orthopedic use falls under autologous, minimally manipulated same-day human cell and tissue product (HCT/P) practice performed outside a Biologics License Application, that is not the same as FDA approval. The FDA has separately warned that many amniotic and umbilical products marketed as “stem cell” injectables are not approved for orthopedic conditions and often do not contain live stem cells [6].
Compared with corticosteroids and HA, orthopedic stem cell injections carry a less mature evidence base and higher out-of-pocket cost.
Prolotherapy Injections: A Different Mechanism
Using an injected irritant, most commonly hypertonic dextrose, it deliberately triggers a localized healing response rather than suppressing inflammation or replacing joint fluid.
The injected solution is thought to induce a controlled inflammatory response that stimulates natural repair, encouraging new connective tissue and reinforcing ligaments and tendons. The exact mechanism remains incompletely understood.
Treatment is typically delivered as a series of injections spaced several weeks apart, unlike the single or short-course regimens used for corticosteroids and HA. Prolotherapy has a smaller, more heterogeneous evidence base than the other injection types covered here.
Some clinical societies do not include prolotherapy in their main orthopedic treatment guidelines, and outcomes appear to depend heavily on protocol and practitioner technique. It is used less often than corticosteroid, HA, or PRP injections in most orthopedic practices.
Which Injection Type Might Be Considered for Knee, Hip, or Shoulder Pain?
Clinical literature suggests injection type selection can vary meaningfully across joint sites. Among the names of injections for knee pain, corticosteroids, HA, and PRP are the most extensively studied options. Corticosteroid relief in the knee tends to be measured in weeks, matching the short-term benefit pattern noted above [1], while HA relief tends to extend over several months [2].
For hip osteoarthritis, corticosteroid injections are commonly used and are often image-guided given the depth of the joint. HA in the hip is off-label in the US — FDA approval covers the knee only — and the 2019 American College of Rheumatology OA guideline strongly recommends against HA for hip OA. Clinicians considering it should weigh that context carefully.
For shoulder problems, first-line care for rotator cuff disease usually centers on physical therapy and activity modification, with a corticosteroid injection as a common adjunct for short-term pain control. In adhesive capsulitis, early intra-articular corticosteroid combined with structured rehabilitation is more standard. PRP and other orthobiologics may be considered in select tendon-related cases.
This is research and clinical-literature context, not prescriptive advice. Individual anatomy, diagnosis, and patient history should guide practitioners’ final decisions on hip, knee, and shoulder pain management.
Preparation, Risks, and Insurance Considerations Across Injection Types
Preparing for joint injections varies by injection type. Corticosteroid and HA injections usually require little preparation, while PRP requires a blood draw and processing time before administration. With prolotherapy, patients are often instructed to avoid anti-inflammatory medications ahead of time, since triggering an inflammatory response is central to how the treatment is intended to work.
Post joint injection treatment guidance is broadly similar: patients are typically advised to rest the treated joint and avoid strenuous activity for a short period. Risks associated with joint injection also vary by category. Corticosteroids carry a low but recognized risk of local joint effects with repeated use; HA is generally associated with mild injection-site reactions; PRP and other orthobiologic products carry the standard risks of any injection, including infection if preparation and handling are not properly controlled.
Insurance considerations are just as variable. Corticosteroid injections, and in many cases HA injections for knee osteoarthritis, are more likely to be covered by insurance once conservative treatment has already been tried — though coverage policies such as L39260 may impose stricter requirements than the FDA label alone. PRP, stem cell, and other orthobiologic injections are typically considered elective or investigational and often not covered by insurance at all. Setting cost expectations with patients before treatment helps avoid friction later.
The contents of this page are meant for licensed medical professionals. They serve informational purposes only and are not to be taken as medical advice.
Citations
[1] Benzon, Honorio T et al. “Use and safety of corticosteroid injections in joints and musculoskeletal soft tissue: guidelines from the American Society of Regional Anesthesia and Pain Medicine, the American Academy of Pain Medicine, the American Society of Interventional Pain Physicians, and the International Pain and Spine Intervention Society.” Regional anesthesia and pain medicine vol. 51,7 746-773. 6 Jul. 2026, doi:10.1136/rapm-2024-105656
[2] Altman, R D et al. “The mechanism of action for hyaluronic acid treatment in the osteoarthritic knee: a systematic review.” BMC musculoskeletal disorders vol. 16 321. 26 Oct. 2015, doi:10.1186/s12891-015-0775-z
[3] U.S. Food and Drug Administration. “Premarket Approval (PMA): Euflexxa (Sodium Hyaluronate) Injection, P010029/S008.” U.S. Food and Drug Administration, www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfpma/pma.cfm?id=P010029S008.
[4] Centers for Medicare & Medicaid Services. “Hyaluronic Acid Injections for Knee Osteoarthritis (L39260).” Medicare Coverage Database, www.cms.gov/medicare-coverage-database/view/lcd.aspx?lcdid=39260.
[5] Hussain, Nasir et al. “An evidence-based evaluation on the use of platelet rich plasma in orthopedics – a review of the literature.” SICOT-J vol. 3 (2017): 57. doi:10.1051/sicotj/2017036
[6] U.S. Food and Drug Administration. “Consumer Alert on Regenerative Medicine Products Including Stem Cells and Exosomes.” U.S. Food and Drug Administration, www.fda.gov/vaccines-blood-biologics/consumers-biologics/consumer-alert-regenerative-medicine-products-including-stem-cells-and-exosomes.
This content was prepared and reviewed under our editorial guidelines , which govern how we source, verify, and update clinical and product information. Every claim is checked against peer-reviewed research, manufacturer documentation, or regulatory guidance before publication.